
White Blood Cell Clues That Change the Differential: Laboratory Insights on WBC Disorders
White blood cell abnormalities can often raise concern during a peripheral blood smear review, but it’s important to remember that a single unusual cell or lab value should rarely be interpreted on its own.
A more reliable approach is to look at the full picture—this includes cell morphology, absolute counts, patient age, clinical context, analyzer flags, and confirmatory testing when needed.
In this laboratory insight review, we’ll walk through several key patterns involving reactive lymphocytes, neutrophils, inherited conditions, viral infections, and blast-like cells.
1. Infectious Mononucleosis Can Be Associated With Hemolytic Anemia
Infectious mononucleosis is commonly associated with reactive lymphocytosis, but an important complication is hemolytic anemia.
A potent cold autoantibody, often demonstrating anti-I specificity, may occasionally develop and produce red blood cell agglutination and clinically significant hemolysis.
Why It Matters
If a patient with a mononucleosis-like illness develops unexpected anemia, red cell agglutination, or laboratory evidence of hemolysis, the possibility of an immune-mediated complication should be considered.
At the Laboratory Bench
Correlate the findings with:
- CBC changes
- Peripheral blood smear appearance
- Evidence of hemolysis
- Appropriate antibody testing
Testing and interpretation should follow the laboratory’s established procedures.
2. Reactive Lymphocytes May Be Seen in HIV Infection
Reactive lymphocytes are not specific to infectious mononucleosis.
HIV infection may also produce reactive lymphocytes, sometimes together with granulocytopenia.
This is an important reminder that peripheral smear morphology can provide clues but usually cannot identify the specific cause of a viral illness.
Why It Matters
Reactive lymphocytes may occur in several infectious conditions. Therefore, identifying reactive lymphocytes on the smear should not automatically lead to a diagnosis of Epstein-Barr virus infection.
At the Laboratory Bench
When reviewing this pattern, consider:
- Absolute neutrophil count
- Other CBC abnormalities
- Clinical history
- Current medications
- Confirmatory virology testing
Key point: A smear finding can support an interpretation, but it should never be used alone to diagnose HIV infection.
3. Infection Can Leave a Characteristic Neutrophil Signature
Neutrophils often develop recognizable changes during infection.
Instead of looking at only one abnormal feature, evaluate the overall neutrophil pattern.
Common findings may include:
- Neutrophilia
- Left shift
- Toxic granulation
- Döhle bodies
- Cytoplasmic vacuolization
Döhle bodies are pale blue, RNA-rich cytoplasmic inclusions that may be seen in neutrophils during infection or other forms of toxic change.
What About Pelgeroid Cells?
Pelgeroid hyposegmentation is not considered a typical infection-related toxic change.
When hyposegmented neutrophils are present, other possibilities should be considered, including:
- Congenital Pelger-Huët anomaly
- Drug-related changes
- Hematologic disease
This distinction is important because hyposegmented cells may be mistaken for immature neutrophils.
4. Neutropenia Is Based on the Absolute Neutrophil Count
A low neutrophil percentage does not necessarily mean that the patient has neutropenia.
The absolute neutrophil count (ANC) should be evaluated.
In this review, neutropenia is defined as:
ANC below 1.5 × 10⁹/L
The ANC may be calculated using:
ANC = WBC × (% neutrophils + % bands) / 100
Laboratory Insight
Always interpret the ANC using your laboratory’s:
- Age-specific reference intervals
- Reporting procedures
- Critical-result policy
The absolute count provides more clinically useful information than the relative neutrophil percentage alone.
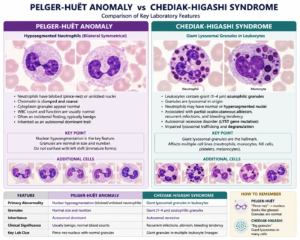
5. Chediak-Higashi Syndrome and Pelger-Huët Anomaly Can Create Diagnostic Mimics
Some inherited leukocyte abnormalities can resemble other hematologic conditions.
Recognizing their characteristic morphology may prevent incorrect interpretation.
Chediak-Higashi Syndrome
Chediak-Higashi syndrome is associated with giant lysosomal granules within leukocytes.
These abnormal granules are associated with abnormal lysosomal trafficking, delayed degranulation, and impaired phagocyte function.
Pelger-Huët Anomaly
Pelger-Huët anomaly produces hyposegmented neutrophils.
These cells may resemble:
- Bands
- Metamyelocytes
- Other immature neutrophil forms
As a result, Pelger-Huët cells may be incorrectly interpreted as evidence of a left shift.
At the Laboratory Bench
When unusual neutrophil morphology is encountered, compare:
- Nuclear maturity
- Granule appearance
- Other blood cell lines
- Patient history
- Previous peripheral smears
Recognition of the overall pattern is more reliable than interpretation of a single cell.
6. Reactive Lymphocytosis With Negative EBV Tests: Consider CMV
A patient may present with a mononucleosis-like illness and reactive lymphocytosis but have negative testing for Epstein-Barr virus.
When both the heterophile antibody test and EBV IgM are negative, another important consideration is cytomegalovirus (CMV).
Testing for CMV IgM may help clarify the cause.
Why It Matters
CMV is a recognized cause of a heterophile-negative mononucleosis-like illness.
The presence of reactive lymphocytes alone therefore cannot determine which virus is responsible.
Serologic results should always be interpreted together with the patient’s clinical findings and according to the laboratory’s confirmatory-testing algorithm.
7. Reactive Lymphocytes and Blasts Can Overlap Morphologically
One of the more challenging areas of peripheral blood smear interpretation is distinguishing a reactive lymphocyte from a blast.
Reactive lymphocytes may sometimes demonstrate features that appear concerning, including:
- Basophilic cytoplasm
- High nuclear-to-cytoplasmic ratio
- Prominent nucleoli
These characteristics alone do not establish that the cell is a blast.
Features That Raise Greater Concern for Blasts
Suspicion increases when the cells demonstrate findings such as:
- Extremely fine chromatin
- A monomorphic cell population
- Abnormal CBC findings
- Significant analyzer flags
Chromatin quality can be an important discriminator, but it should not be used by itself.
Never identify a blast based on only one morphologic feature.
Review the complete peripheral smear and escalate suspicious cells according to the laboratory’s standard operating procedure.
8. Understanding the Neutrophil Respiratory Burst
Neutrophils use an oxygen-dependent mechanism to help destroy microorganisms.
During the respiratory burst, NADPH oxidase initiates the production of reactive oxygen species.
A simplified pathway is:
Oxygen → Superoxide anion → Hydrogen peroxide
Two important products emphasized in this process are:
- Superoxide anion
- Hydrogen peroxide
These oxidants contribute to intracellular microbial killing by neutrophils.
Important Neutrophil Granule Fact
Another useful laboratory fact involves the contents of neutrophil primary granules.
Myeloperoxidase is present in the primary, or azurophilic, granules of neutrophils.
Primary granules also contain substances such as:
- Lysozyme
- Acid phosphatase
Understanding neutrophil granules and their functions helps connect cellular morphology with normal neutrophil physiology.
A Safer Approach to WBC and Peripheral Smear Review
When reviewing abnormal white blood cell findings, use these five checks:
1. Confirm the Absolute Count
Do not rely only on percentages. Calculate or verify clinically important absolute counts such as the ANC.
2. Assess the Entire Smear Pattern
Look at the overall cellular population rather than interpreting one abnormal-looking cell in isolation.
3. Separate Toxic Changes From Inherited Mimics
Toxic granulation, Döhle bodies, and vacuolization may accompany infection, while findings such as Pelger-Huët morphology require a different interpretation.
4. Correlate With Age and Clinical Context
Patient age, history, medications, and clinical findings can significantly change the interpretation of the laboratory picture.
5. Escalate Suspicious or Discordant Findings
When morphology does not match the CBC, analyzer findings, or expected clinical picture, additional review may be necessary.
Suspicious blast-like cells should be handled according to laboratory SOP.
Test Your Knowledge
1. Which complication may occasionally occur in infectious mononucleosis?
Answer: Hemolytic anemia
A strong cold autoantibody, often with anti-I specificity, may cause red cell agglutination and hemolysis.
2. Which peripheral smear finding may be seen in HIV infection?
Answer: Reactive lymphocytes
HIV may be associated with reactive lymphocytes and granulocytopenia, although morphology alone is not diagnostic.
3. Which inclusion may be found in neutrophils during toxic change?
Answer: Döhle bodies
These are pale blue, RNA-rich cytoplasmic inclusions.
4. Which enzyme is present in primary neutrophil granules?
Answer: Myeloperoxidase
Primary azurophilic granules contain myeloperoxidase, lysozyme, and acid phosphatase.
5. Which finding is NOT a typical neutrophil response to infection?
Answer: Pelgeroid hyposegmentation
Pelgeroid cells may be associated with congenital Pelger-Huët anomaly, medications, or hematologic disease.
6. According to this review, when is neutropenia present?
Answer: ANC below 1.5 × 10⁹/L
Neutropenia should be evaluated using the absolute neutrophil count rather than the neutrophil percentage alone.
7. What morphology is characteristic of Chediak-Higashi syndrome?
Answer: Giant lysosomal granules
These abnormal granules are associated with abnormal lysosomal trafficking and impaired phagocyte function.
8. Pelger-Huët anomaly must be distinguished from what common hematologic pattern?
Answer: A left shift
Hyposegmented neutrophils may resemble bands or other immature neutrophils.
9. Reactive lymphocytosis with negative heterophile and EBV IgM tests suggests testing for what?
Answer: CMV IgM
CMV is an important cause of heterophile-negative mononucleosis-like illness.
10. Which products are central to the neutrophil respiratory burst?
Answer: Superoxide and hydrogen peroxide
NADPH oxidase generates superoxide, which can be converted into hydrogen peroxide as part of intracellular microbial killing.
Laboratory Insights
White blood cell morphology provides valuable laboratory clues, but morphology should always be interpreted together with quantitative results and clinical information.
Remember these important points:
- Mononucleosis can occasionally be complicated by hemolytic anemia associated with cold autoantibodies.
- Reactive lymphocytes are not specific for EBV and may also occur in HIV and CMV infections.
- Infection-related neutrophil changes include toxic granulation, Döhle bodies, vacuolization, neutrophilia, and left shift.
- Neutropenia should be assessed using the absolute neutrophil count.
- Pelger-Huët anomaly may mimic a left shift.
- Chediak-Higashi syndrome is associated with giant lysosomal granules.
- Reactive lymphocytes and blasts may overlap morphologically, so suspicious cells require complete smear assessment.
- Superoxide and hydrogen peroxide are important products of the neutrophil respiratory burst.
The central laboratory principle is simple: recognize the pattern, question the mimic, and correlate the result.
Educational Note: This article is intended for medical laboratory science education and review. Laboratory findings should be interpreted according to institutional procedures, validated reference intervals, and appropriate clinical correlation.